Survey
* Your assessment is very important for improving the work of artificial intelligence, which forms the content of this project
Staying in Step
A quarterly newsletter from the
Florida Hospital Parkinson Outreach Center
Fall 2013
Sexuality and Intimacy in Parkinson’s
A Quality of Life Issue
Treatments for Parkinson’s disease are often centered on addressing motor symptoms despite the fact that many
of the non-motor or motor-related symptoms can have the greatest impact on a person’s quality of life. Psycho
-social and relationship issues are often overlooked in the treatment plans of people with Parkinson’s disease,
and are often not discussed with the treating physician; even though they are central to their wellbeing, and
often significantly impacted by the disease’s course. Sexuality is a complex process that encompasses a
person’s physiological, mental, psychological, relational and cultural make up. Sexuality can be significantly
impacted by Parkinson’s and its treatment with age, disease severity, depression, apathy and use of medications
as the greatest predictors of sexual wellbeing for those with the disease. While often not openly discussed,
intimacy and sexuality is of crucial concern and directly related to quality of life. Having a satisfying intimate
life is an important aspect of feeling normal when so many things have changed.
Parkinson’s disease often changes the dynamics of relationships with the care partner often taking on more
responsibilities and taking on the role of “care provider” instead of partner and spouse. Overseeing medications
and doctor’s appointments in the beginning stages, to more hands-on care later in the disease, causes the focus
to be on meeting basic needs and less on relationships and intimacy. While some couples can easily adapt to
limitations or cessation of sexual intimacy caused by having a chronic illness, others find this a source of
frustration and stress with a loss of self-esteem. Sexuality is often equated with sexual intercourse and sexual
functioning; however, it is important to understand that this is only one dimension of sexuality and intimacy.
Intimacy between a couple can be a time of sharing and touching which can improve the quality of the
relationship and improve sense of well-being. Try sitting together in a non-demanding way and spend time
cuddling and focusing on each other as individuals. Touch is powerful and can be very intimate and rewarding.
Touch helps us to feel connected, bonds us closer to our loved ones, reduces anxiety and give our brains the
sensory input it needs.
Very few patients receive help for their sexual concerns with many people feeling embarrassed, anxious or that
their concerns about sex are inappropriate. However, sexual dysfunctions are often related to their medical
condition or treatments. Physicians often do not address sexual concerns during office visits due to time
constraints, complexity of the illness, and confusion about how to approach the conversation or a lack of
knowledge about sexuality and how to address it.
Contined on page 2...
Sexuality and Intimacy in Parkinson’s continued from page 1
In addition, couples often have difficulty talking openly with each other about sex, especially those
patients who may have a difficult time expressing themselves. There are effective treatments
available for many sexual problems; however, the effectiveness of treatment including
pharmacological or psychological methods depend on a thorough history with the patient and
partner. Dysfunctions can include: decreased desire called Hypoactive Sexual Desire Disorder,
increased sexual desire or hyper sexuality, sensory changes, painful intercourse, erectile
dysfunction, and inability or limitation in giving intimate touch, to name a few.
Even if your physician does not initiate a discussion on intimacy and sexuality issues, there are
ways you can address these concerns with your physician.
Start by choosing a health care professional you have confidence in.
Be upfront about your concerns-your intimate life has a profound effect on your quality of life.
Decide whether you want to address this subject alone or together with your partner.
Start the conversation by saying…”I have heard that people with PD experience changes in
their sexual function. Can I discuss this delicate issue with you?”
If he/she is open to this discussion describe the nature of your problem in simple terms.
If they are unable to address this themselves, ask your physician to refer you to someone you
can address the problem with.
Ask about available treatment options including anticipated results and side-effects.
Sexual intimacy should not be a taboo topic as it is an important aspect of quality of life and
relationships affected by Parkinson’s disease. Those with Parkinson’s and their partners should be
encouraged to discuss these issues and concerns with their health care professionals and highlight
the importance of treating such aspects of the disease.
Source: Adapted from the National Parkinson Foundation Parkinson Report Fall 2006
Important Resources
On the Web:
www.ageinplace.org
This is a website from the National Aging in Place council that provides a list of services available
by area dedicated to meeting needs in order to “age in place”. The website offers information on
such things as home remodeling, elder law, home care, emergency response systems, etc.
MWPF.org: Melvin Weinstein Parkinson’s Foundation
This foundation provides assistance with the cost of medical equipment. The site also offers
information on prescription assistance.
Eldercare.gov: This website is a public government site that connects people to available services
by area. Topic specific search including: caregiving, housing options, legal assistance, long-term
care and transportation.
Local Resources:
Share the Care: Offers adult day care, care management, counseling, crisis care and respite
services. Contact number is 407-423-5311
ITN Orlando: Independent Transportation Network is a transportation service that serves the
Metro Orlando area. Members pay an annual fee of $60 and can be transported 24 hours a day for
any service, door to door in personal automobiles, not buses. Fees are $4.00 pick up fee and $1.50
a mile. For more information call: (407) 228-7761
For additional resource information, call the Parkinson Outreach Center at 407-303-5295
Know the Lingo: PD Glossary of Terms/Slang
PwP-Person with Parkinson’s. A common way of referring to someone with PD.
Carbidopa-Levodopa- A drug combination of L-dopa, the brain chemical dopamine and a drug
that improves the effectiveness of levodopa. The combination is called Sinemet®.
Dyskinesia– Abnormal muscle movements that may appear as a side effect of Levodopa.
Freezing– A temporary, involuntary inability to move; a feeling of being stuck.
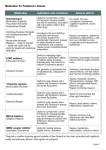
Parkinson’s Medications At-A Glance
Class/Type of Medication
What You Should Know
How it Works
Levodopa
Carbidopa/Levodopa (Sinement®)
Carbidopa/Levodopa controlled release
(Sinement CR®)
Carbidopa/Levodopa oral disintegrating tablet
(Parcopa®)
Carbidopa/Levodopa/Entacapone (Stalevo®)
Dopamine Agonists
Apomorphine (Apokyn®)
Bromocriptine (Parlodel®)
Pramipexole (Mirapex®)
Ropinirole (Requip®)
Ropinirole extended-release tablet
(Requip®XL™)
Rotigotine transdermal system (Neupro®)
The most potent and effective
medication for Parkinson’s.
Considered the gold standard
for Parkinson’s with the
broadest antiparkinsonian
effects of any treatment
Neurons convert Levodopa to
dopamine. Levodopa replaces
dopamine lost by Parkinson’s.
Carbidopa is combined to prevent
nausea and ensure the levodopa is not
metabolized before it enters the
brain.
This class of medications, in
general, are not as effective in
relieving symptoms of
Parkinson’s as Carbidopa/
Levodopa. Doctors often
prescribe agonists as initial
therapy in Parkinson’s or as a
complement to levodopa in
people who have fluctuations of
symptoms. They are started in
low doses with gradual increase
in dosage to prevent side
effects.
Used primarily to help with
wearing-off, when levodopa
becomes short-lived.
Dopamine agonists are drugs that
stimulate the parts of the brain that
are influenced by dopamine. The
brain is tricked into thinking it is
receiving dopamine.
COMT Inhibitors
Entacapone (Comtan®)
Tolcapone (Tasmar®)
MAO-B Inhibitors
Rasagiline (Azliect®)
Selegiline or deprenyl (Eldepryl®)
SelegilineHCI orally disintegrating tablet
(Zelapar®)
Anticholinergics
Benztropine mesylate (Cogentin®)
Trihexyphenidyl (Artane®)
Other
Amantadine (Symmetrel)
Rivastigamine Tartrate (Exelon®)
These drugs have modest effect
in suppressing the symptoms of
Parkinson’s. They delay the
need for levodopa when
prescribed in the earlier stages
of Parkinson’s and are approved
for use in later stages of PD to
boost the effects of levodopa.
The oldest medications for
Parkinon’s but no longer widely
used. Used for people with
early onset PD who experience
mainly tremor. May ease
dystonia associated with
wearing-off or peak-dose
effects.
In the early stages of PD,
Amantadine is used to help
tremor. In later stages, it has
also been found useful in
reducing dyskinesias. Excelon
is approved for the treatment of
dementia in PD.
COMT Inhibitors represent the
newest class of Parkinson’s
medications. These agents have no
direct effect on PD symptoms, but
instead are used to prolong the effect
of levodopa by blocking metabolism.
MAO-B Inhibitors block an enzyme
in the brain that breaks down
levodopa.
Do not act directly on the
dopaminergic system. Instead, they
decrease the activity of acetylcholine
that regulates movement and
memory.
Amantadine promotes the release of
dopamine from nerve terminals,
blocks the re-uptake of dopamine and
functions as an inhibitor of a
glutamate receptor. Exelon inhibits
enzymes that break down
acetylcholine.
Events and Activities
Ride with Larry, a documentary film being featured at the Orlando Film Festival on October
19th at 4:45 pm, at the Plaza Cinema Café. This film chronicles Larry, a retired police captain with
Parkinson’s for over 20 years who bikes across South Dakota to show the power of keeping your body
active and mind positive, proving that the best cure is living life to its fullest.
For Sale: Equipment and medical supplies are available including: Wheelchairs, walkers, portable
ramps and many other items. Call the POC at 407-303-5295 for more information.
First Deep Brain Surgery by Robotics at Florida Hospital Celebration Health
A patient at Celebration Health , one of our very own from the Altamonte/Longwood support
group, was the world’s first to receive deep brain stimulation (DBS) using Mazor Robotics
Renaissance Guidance System. Dr Nizam Razack, MD performed the procedure in August with
several successful surgeries since that time.
DBS is a procedure to implant a battery-operated medical device in the brain to deliver electrical
stimulation to block abnormal nerve signals that cause the debilitating neurological symptoms of
Parkinson’s disease and essential tremor. The use of Renaissance’s proprietary pre-operative planning
software allows surgeons to determine the optimal trajectory for implanting the electrodes before
beginning the surgery and then use the guidance unit to execute the implantation with precision.
“Mazor Robotics Renaissance increases guidance accuracy during the procedure and adds an extra
element of safety for patients undergoing this major operation,” said Razack. “The technology also
allows for less time in the operating room.”
When asked about the experience, Clare Beslack, the first in the world to have this surgery. said,
“I did not know at first I would be having my surgery done with a robot. When Dr Razack came out
after surgery and told my husband and daughter, they were so excited that I was the first.” When
asked about the length of time the surgery took, Clare stated, “I do not know how long I was in
surgery because of going to radiology for several scans. They did tell me the surgery took 29 minutes
less with the robot.” Clare feels like the surgery has been a success, “The result is excellent. I am
moving better. I have some of my functionality back. I am starting to decrease my medicine, which
is going to be great.”
Wellness Programs
MVP-Movement is Vital for Parkinson’s is a new 8 week program that focuses on improving
movement, balance, and coordination. Class sessions are every Tuesday and Thursday from 2:003:00pm at Lee Rd location, starting on September 24th through November 14th. For all levels of
disease severity, the sessions will include: Boxing, Power moves, Mighty Muscles, and Ballers. All
functional exercises target balance, strength, endurance, coordination, spatial awareness are give you
exercises you can continue to do at home. For more information or to register, call Florida Hospital
Sports Medicine and Rehab at 407-303-8041. Scholarship available, contact 407-303-5295 for
information to apply.
Pedaling for Parkinson’s-A designated spin class for those
with Parkinson’s and their care partners held at the Crosby
Comic Cures
Wellness Center in Winter Park, Monday, Wednesday and
Friday from 2:00-3:00 pm. Contact the Crosby Center for
information at: 407-644-3606.
Dance for Parkinson’s-A dance class offered in partnership
with the Parkinson Outreach Center and Rollins College for all
levels of disease severity. Modeled after the Dance for PD®
program in NY, dance develops flexibility, addresses balance,
stimulates the mind and encourages socialization. Classes are
held on the 1st and 3rd Thursday of each month at the Florida
Hospital Church from 1:00 pm to 2:15. Call 407-303-5295 for
more information.
CHEER>UP-A drama therapy group that uses theater
techniques such as humor, improvisation, pantomime, vocal
readings, and more to address mood, voice, movement and
socialization. Classes are held at the Florida Hospital Church
and are FREE. Call 407-303-5295
Parkinson Research News
Living Cell Technologies Implants First Person with Potential Parkinson’s Treatment
The first patient ever to be successfully implanted in the Phase I clinical trial of the regenerative cell
therapy NTCELL® – a potential treatment for Parkinson’s, has recovered well so far. The surgery was
conducted at Auckland City Hospital, in New Zealand
In the clinical trial, NTCELL is injected under guidance by neuroimaging into the affected area of the
human brain where substantial death of neurons and other cells has occurred. An MRI scan taken the day
after the surgery indicated that the NTCELL capsules have been implanted at their intended target.
LCT's Phase I clinical trial is an open label investigation of the safety and clinical effect of NTCELL in
four people who have been diagnosed with Parkinson’s disease for at least four years. The first patient will
now be monitored for two months to confirm no serious adverse safety events.
Source: proactiveinvestors.com
The Effect of Ten Years with Parkinson’s Disease
A large number of people who had Parkinson's Disease for more than ten years were assessed
to see what effect it had on them. The clinical status and health-related quality of life of
patients reaching this milestone had not been well documented before. Their average age was
68 years old. Their average age of onset was 53 years old. Their average disease duration
was 14 years. Many of them were minimally disabled (44%) or experiencing postural
instability (40%). Most (88%) were able to stand unaided but falls were common (55%).
Almost all (93%) were living at home, with a family member as a regular caregiver (84%).
They had an average of two additional medical disorders with arthritis (49%) and heart
problems (32%) being the most common. Most of them (87%) took at least 2 medications,
with L-dopa (96%), dopamine agonists (45%) and antidepressants (37%) being the most
common. Most of them were not currently utilizing physical, occupational or speech therapy,
but two-thirds of them reported engaging in physical activity. Deep brain stimulation was
documented in 22%. Overall the mean health-related quality of life and caregiver burden was
impaired in all domains.
Source: Parkinsonism Related Disorders [2012] 18 supplement, 3 : S10-S14 28 (3) : 380-383 (A.Hassan, S.S.Wu, P.Schmidt, I.A.Malaty, Y.F.Dai,
J.M.Miyasaki, M.S.Okun), viartis.net
Parkinson’s Disease With Freezing of Gait Associated with REM Sleep Disturbance
People with Parkinson’s disease (PD) who experience freezing of gait, a common symptom
of the disease as it advances, are more likely to experience disturbed rapid eye movement
(REM) sleep, according to a study published in the August 14 online edition of Neurology.
REM sleep is best known as the dream phase of sleep, during which people experience rapid
movement of the eyes, but very little activity in other muscles. When this phase of sleep is
disturbed, it is called REM sleep behavior disorder (RBD) which can be disruptive and cause
harm to themselves or bed partners. RBD is associated with the development of Parkinson’s
disease and may be an early non-motor sign of the disease. The study explored the relationship
of PD with freezing of gait and increased muscle activity during REM sleep. It was led by
Aleksandar Videnovic, M.D., M.Sc., Assistant Professor of Neurology at Northwestern
University Feinberg School of Medicine. The team of researchers conducted sleep studies, in
which brain, heart, breathing and muscle activity are monitored, in four groups: 1) people with
RBD only 2) people with PD with freezing of gait; 3) people with PD without freezing of gait;
and 4) controls.
The results found study participants with PD and freezing of gait had threefold greater
muscle activity during REM sleep than participants with PD without freezing of gait.
Participants with PD with freezing and participants with REM sleep behavior disorder showed
similar increased muscle activity during REM sleep. This study provides further evidence of a
relationship between freezing and increased muscle activity during REM sleep. First, it
suggests that sleep studies may be able to identify which people with PD are more likely to
experience freezing of gait. This will have to be confirmed in other studies. Second, it may
shed light on the biological mechanism of freezing. It is possible that RBD and freezing of gait
share the same biological mechanism, as they tend to co-occur.
Source: PDF
Florida Hospital Parkinson Outreach Center Support Group Meetings
The Florida Hospital Parkinson Outreach Center hosts monthly support group meetings
for people with Parkinson’s disease and their loved ones. All meetings are free to attend!
3 Locations to serve you!
Downtown Orlando:
Florida Hospital Seventh-Day Adventist Church, 2800 N Orange Ave, Orlando, FL 32804
(Corner of Orange Ave and King Street) Days: 2nd and 4th Thursday each month
Time: 10:00 am-12:45 pm includes support group discussion, educational lecture or music therapy, exercise
class and caregiver break-out sessions.
Altamonte Springs/Longwood:
St Stephen’s Lutheran Church, 2140 W SR 434, Longwood, FL 32701
Days: 2nd and 4th Tuesday each month
Time: 10:00 am-12:45pm includes support group discussion, educational lecture or music therapy, exercise
class and caregiver break-out session once a month
Winter Garden/West Orange:
Golden Pond Communities 402 Lakeview Rd, Winter Garden, FL 34787
Day: 4th Wednesday of each month
Time: 10:30am -12:00 pm includes discussion and educational presentation
CHEER>UP Drama Therapy Group:
Florida Hospital Seventh-Day Adventist Church, 2800 N. Orange Ave, Orlando, FL 32804
Day: 3rd Tuesday of each month from 2:00 pm to 3:00 pm.
Dance for Parkinson’s
Florida Hospital Seventh Day Adventist Church, 2800 N Orange Ave, Orlando FL 32804
1st & 3rd Thursday of each month. Call POC for registration and fees. 407-303-5295
1685 Lee Rd, Suite 110
Winter Park, FL 32789
The Parkinson Outreach Center
is now on Facebook! Like us
and keep updated on what’s
going on!